CHAGAS DISEASE
A silent parasite colonizes and degrades the heart tissue, leading to progressive disease and high mortality

Persists within cardiac tissue and progressively damages myocardium over ~10–30 years

~30% of cases: arrhythmia, cardiac arrest, cardiomyopathy, heart failure, emboli, and other conditions

Additional organ systems vulnerable: GI (megacolon, megaesophagus), CNS

Other forms of transmission: mother to child, blood donation, organ transplant, food-borne
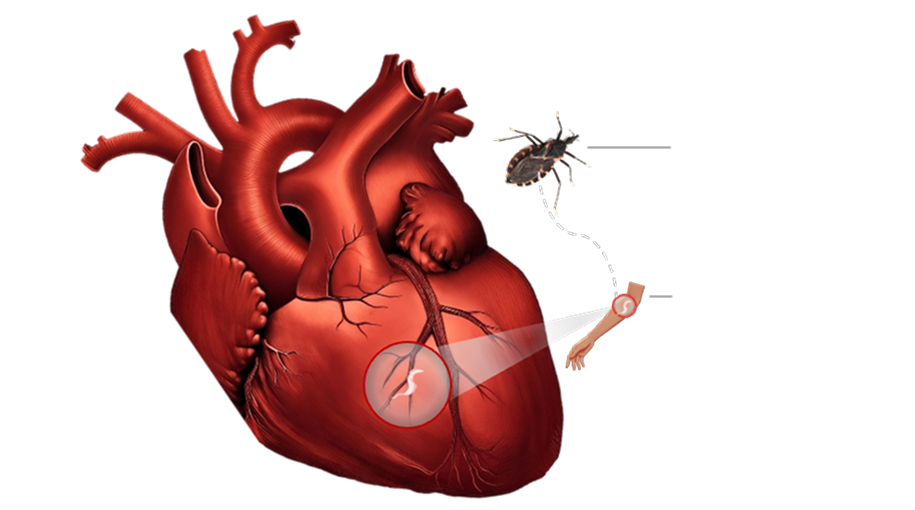
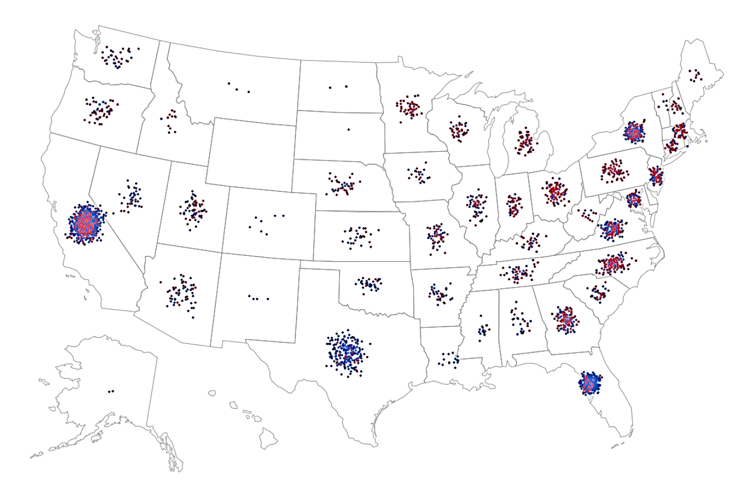
T. cruzi replicates within heart muscle cells, digestive tract tissue, and other organs. Cells eventually burst open, allowing T. cruzi to spread to new sites. Twenty to thirty percent of those infected will eventually develop severe cardiac or gastrointestinal disease (e.g., sudden cardiac arrest, heart failure, stroke, or life-threatening GI enlargement), and ~30% will progress to Chagas cardiomyopathy, a chronic, destructive condition that can lead to sudden death. There is no way to predict who will progress, creating a strong imperative to treat all infected individuals.
There are no FDA-approved treatments for adults with chronic Chagas disease.
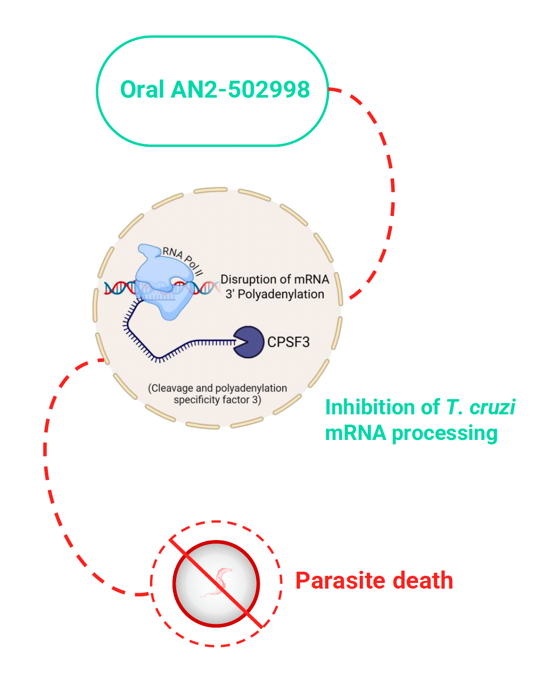
AN2-502998: An oral, small molecule benzoxaborole targeting CPSF3
AN2-502998 is an oral benzoxaborole with presumed mechanism of action being inhibition of CPSF3 in the T. cruzi parasite.
Preclinical highlights
Curative potential observed in multiple non-human primate studies.
Kills both actively dividing and dormant parasites faster than benznidazole in preclinical models.


A Phase 2 proof-of-concept trial is anticipated to initiate in 2026, with topline data expected in the second half of 2027.